
Loading your page…
Loading your page…
Published by Committee for the Promotion of Remote Surgery Implementation, Japan Surgical Society
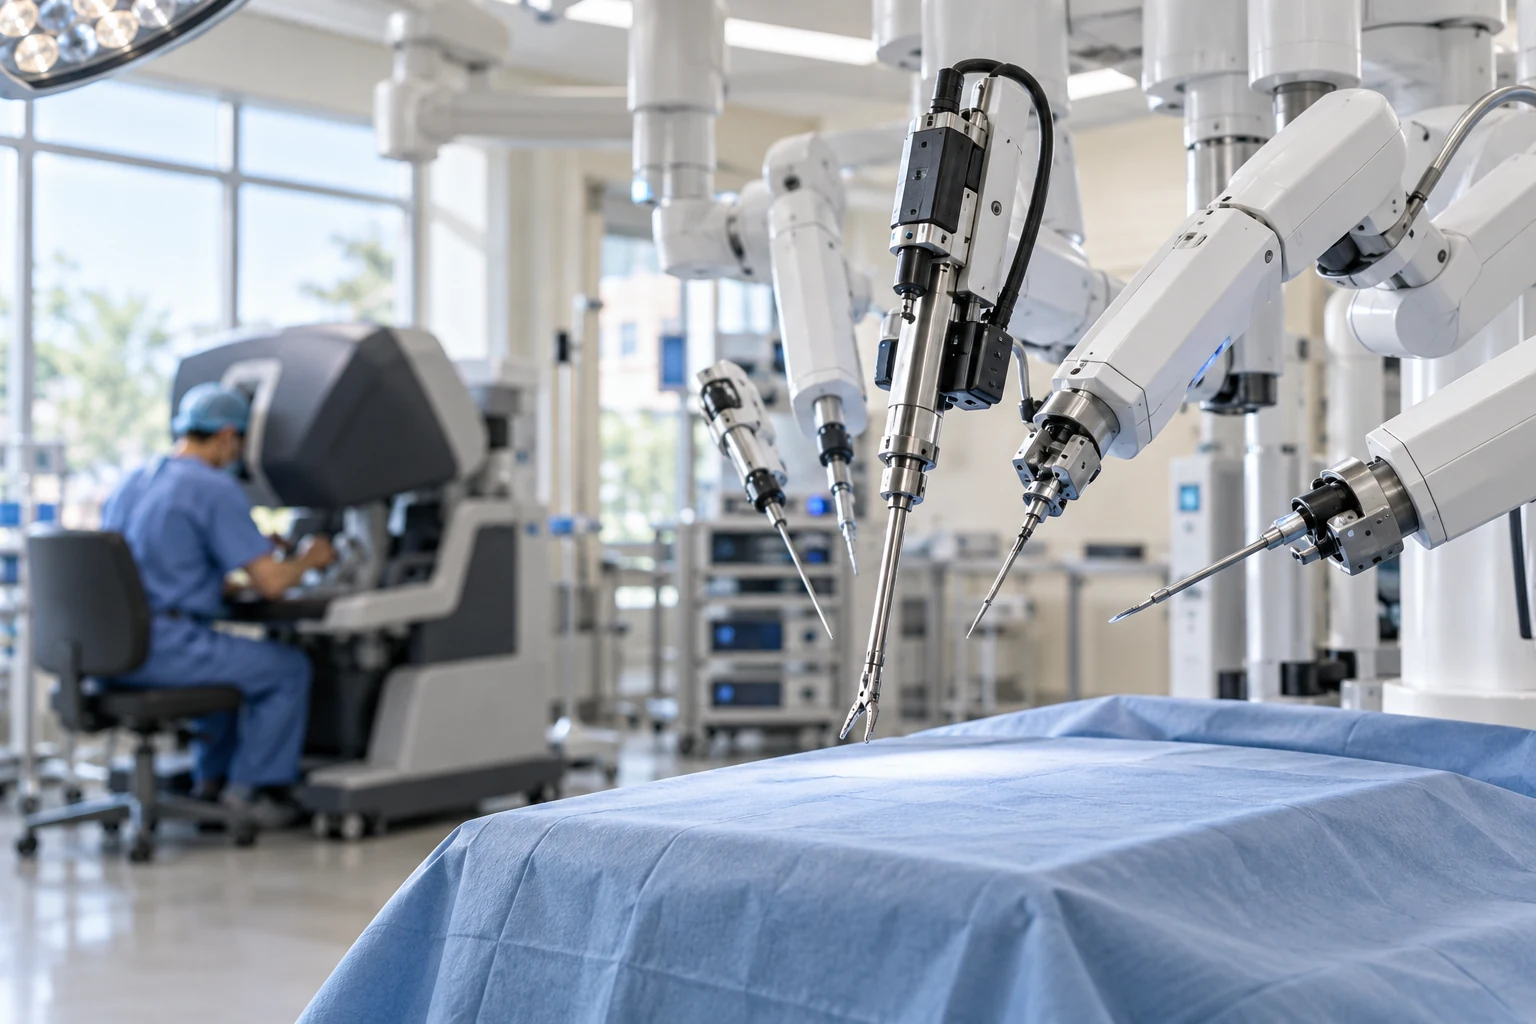
This document outlines the clinical practice guidelines for telesurgery in Japan (2nd Edition). It details requirements for surgical teams, facilities, and communication networks for three types of telesurgery: telementoring, telesurgical support, and full telesurgery. It provides specific safety, information security, and legal accountability standards.
Key Takeaways
Compared to the first edition, the second edition updates and expands implementation-oriented guidance [27, 28]. Key changes include: 1) Concrete qualification requirements for surgeons and support staff [27, 28]; 2) Detailed institutional and network environment specifications [27, 28]; 3) Expanded cybersecurity standards [27, 28]; 4) Registry-based governance requiring performance reporting [29]; 5) Inclusion of representative informed consent templates and contractual frameworks [27, 28]; and 6) Separation of universally applicable technical/legal principles from Japan-specific regulatory systems to improve international applicability [27, 30].
A remote surgeon must possess sufficient technical skills to safely perform telesurgery while supporting a local surgeon, hold certification as a robot-assisted surgery instructor/proctor or an equivalent qualification corresponding to the specific surgical robot model, and complete the Training Program for Remote Surgery managed by the Japan Surgical Society [1].
The local surgeon must complete the robot manufacturer's training, obtain an operator certificate, complete the Training Program for Remote Surgery, hold board certification in their field, and have experience with the planned procedure or prior direct instruction from a certified instructor [2].
Clinical engineers experienced in surgical robot maintenance and management must be assigned to both local and remote facilities, and must complete the manufacturer's training program and the Training Program for Remote Surgery [3].
The local facility must possess the equipment and staff necessary to complete robotic surgical procedures planned for telesurgical support through alternative approaches, such as endoscopic surgery or open surgery, in case telesurgical support cannot continue [4].
The sum of the round-trip communication network transmission delay time and information processing delay time newly generated in the telesurgery environment should be within 100 ms (0.1 s) at the maximum [5].
A closed communication network, such as a layer-3/layer-2 virtual private network (L3/L2VPN), that is physically or logically separated from the Internet is desirable [6]. If open lines are unavoidable, highly secure IPSec+IKE (version 2) connections are recommended with strict source/destination IP and port firewall limits [6].
The local surgeon, local surgical staff, and remote surgeon must hold a conference in advance to discuss the appropriateness of telesurgical support, division of roles, potential surgical procedure changes, and response plans if telesurgery becomes unfeasible, and document this in the medical record [7].
In principle, the local surgeon and local facility administrator bear responsibility for telesurgical support outcomes, and must discuss responsibility sharing with the remote surgeon and remote facility administrator for each case and create a written agreement in advance [8, 9].
Telementoring does not require strict delay time management like telesurgical support, but perceived delay must be evaluated in advance [10]. A total delay time of <= 450 ms is recommended as a reference [10].
Clinical Topic
Telesurgery (Remote Surgery)
Objectives
To present appropriate standards for the systems through which telesurgery is provided and implemented, specifically when performed remotely by a supervising physician in a distant location using both surgical robots and information and communication technology.
Target Patient Population
Patients undergoing surgical procedures that can be performed remotely using robotic systems.
Target Providers
Therapeutic Area
SurgeryGuideline Scope
Inclusion Criteria
Exclusion Criteria
Care Settings
Special Populations
Contraindications
Monitoring Guidance
Continuous monitoring of patient's vital signs (such as ECG and blood pressure) by the local surgeon and anesthesiologist is required, with remote surgeons/mentors recommended to continuously monitor this information via a separate communication line.
Difficulty
advanced
Learning Paths